Welcome to the 2026 Interprofessional Cross-Campus Collaborative Case
This case collaborative provides you with the opportunity to work in an interprofessional team of students from different health and social care professions.
Working together, your team will identify the needs of Daijha Flores and her family and will build an interprofessional team to meet their needs.
Your team is tasked with ensuring the delivery of holistic, whole person, interprofessional team-based care to meet the physical, emotional and social needs of Daijha Flores and her family.

Case timeline - Missouri/Arkansas
Registration:
Registration opens Friday, August 28, 2026
Orientation:
- Wednesday, Oct. 07, 7:30 - 8:30 p.m. Live via Zoom
Workshops:
- Workshop 1: Whole Person Healthcare
- Workshop 2: Roles & Responsibilities
- Workshop 3: Cochlear Implants
(Each of these workshops will be available on the case website to view on demand until October 16, 2026.)
Practice Sessions:
- October 26th through November 6, 2026 Live via Zoom
Final Presentations:
- Week of Nov. 9 - Nov. 12, Live via Zoom
Reflection and Recognition Reception:
- Wednesday, Nov. 18, 7:30 - 8:30 p.m., Live via Zoom
Case timeline - Arizona
Registration:
Registration opens Friday, August 28, 2026
Orientation:
- Wednesday, Oct. 07, 5:30 - 6:30 p.m. Live via Zoom
Workshops:
- Workshop 1: Whole Person Healthcare
- Workshop 2: Roles & Responsibilities
- Workshop 3: Cochlear Implants
(Each of these workshops will be available on the case website to view on demand until October 16, 2026.)
Practice Sessions:
- October 26th through November 6, 2026 Live via Zoom
Final Presentations:
- Week of Nov. 9 - Nov. 12, Live via Zoom
Reflection and Recognition Reception:
- Wednesday, Nov. 18, 6:30 - 7:30 p.m., Live via Zoom
Case timeline - California
Registration:
Registration opens Friday, August 28, 2026
Orientation:
- Wednesday, Oct. 07, 5:30 - 6:30 p.m. Live via Zoom
Workshops:
- Workshop 1: Whole Person Healthcare
- Workshop 2: Roles & Responsibilities
- Workshop 3: Cochlear Implants
(Each of these workshops will be available on the case website to view on demand until October 16, 2026.)
Practice Sessions:
- October 26th through November 6, 2026 Live via Zoom
Final Presentations:
- Week of Nov. 9 - Nov. 12, Live via Zoom
Reflection and Recognition Reception:
- Wednesday, Nov. 18, 5:30 - 6:30 p.m., Live via Zoom

Your Team Task:
Your team is about to take over the care of 14-year-old Daijha Flores, who was seen in the Emergency Department following a motor vehicle accident in which the vehicle she was in was T-boned. Daijha presented with left-sided mouth pain, having difficulty hearing despite a left cochlear implant, pain and bruising over the left collarbone and hip, pain with a laceration on the right hand, and edema of the right 5th finger. ED findings included concussion without loss of consciousness; laceration of right hand; displaced fracture of the base of the 5th metacarpal bone of the right hand; left hip contusion; left clavicle contusion; tooth fracture and oral cavity laceration and unspecified sensorineural hearing loss establishing need for evaluation of cochlear implant device.
You are provided with the following information to help you with your task.
- Written narrative from patient Daijha Flores, mother Sophia Flores, and younger sister Andrea Flores.
- A description of Daijha Flores’ hometown.
- Documentation from the health professions involved in Daijha’s care during her Emergency Department visit and subsequent follow up care.
Your team is tasked with:
- Identifying the holistic needs of Daijha Flores and her family.
- Building an interprofessional team with the skills to meet the needs of Daijha Flores and her family
- Presenting the designed interprofessional total care team for the case to a panel of healthcare professionals.
As you work together to build the team to care for Daijha Flores and her family you must consider:
- The holistic needs of Daijha Flores and her family.
- How you can place the interests of Daijha and her family at the center of the interprofessional team.
- The composition of the interprofessional team, identifying the roles and responsibilities of those involved and how they relate to the identified needs for this family.
- Specific team strategies you will use to ensure the interprofessional team functions as an effective team.
- Specific communication strategies the team will use to ensure they practice effective interprofessional communication.
- How quality improvement and patient safety will be addressed by the team.
THE CORE COMPETENCIES FOR INTERPROFESSIONAL COLLABORATION
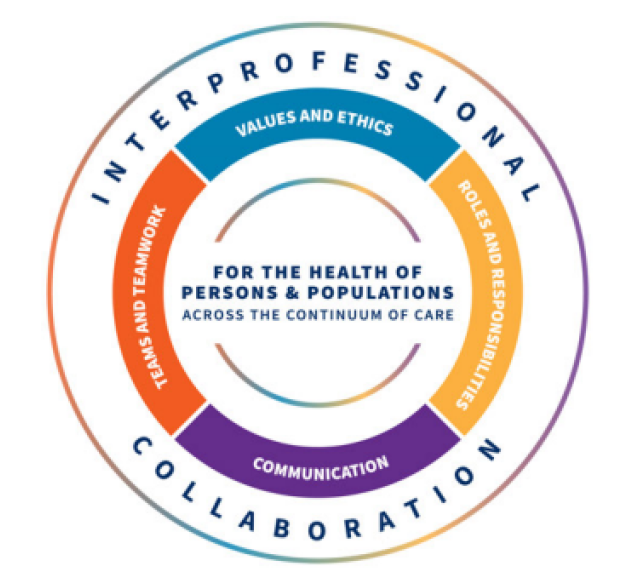
Use the 4 core competencies for interprofessional collaborative practice to guide you on the issues to consider
- Work with individuals of other professions to maintain a climate of mutual respect and shared values. (Values/Ethics for Interprofessional Practice)
- Use the knowledge of one’s own role and those of other professions to appropriately assess and address the health care needs of patients and to promote and advance the health of populations. (Roles/Responsibilities)
- Communicate with patients, families, communities, and professionals in health and other fields in a responsive and responsible manner that supports a team approach to the promotion and maintenance of health and the prevention and treatment of disease. (Interprofessional Communication)
- Apply relationship-building values and the principles of team dynamics to perform effectively in different team roles to plan, deliver, and evaluate patient/population-centered care and population health programs and policies that are safe, timely, efficient, effective, and equitable. (Teams and Teamwork)

Teams
Once you register for the collaborative event, you will be placed into a small interprofessional team and will be assigned a team facilitator. Names and contact information for your teammates and facilitator will be sent to you prior to orientation. By the end of the orientation event, your team should have developed a plan as to how you will communicate and function to complete the assigned tasks.
Interaction with Facilitators
A faculty team facilitator will be assigned to each team. The faculty team members who developed the case will serve as facilitators for your group and can help guide you through the task. So please feel free to ask for help in understanding the assigned task. Your facilitator is able to:
- Provide feedback/guidance to your team as you work through the case and prepare your presentation.
- Review your plan/presentation prior to your final team presentation.
- Provide feedback and comments during your practice session.
The Presentations
Your end product is an oral presentation, presented via Zoom, which demonstrates your reflection on the life story and care of Daijha Flores and her family, and the professionals you would include in an interprofessional team to meet their needs.
You are also asked to provide a short reflective piece in your presentation on your own team's experience of collaboration in action, including what you have learned about the other professions' roles and responsibilities, team working, and communication issues.
Presentation Structure
Each team will have 20 minutes to present their work. A 5-minute, 3-minute and 1-minute warning will be given to the team. At the conclusion of 20 minutes, the timekeeper will announce time and your team must stop their presentation. No team will be permitted to exceed the allocated 20-minute time limit. If the team completes its presentation prior to the 20-minute time limit, the team should announce that they have completed their presentation. Presentations will be followed by a 10-minute question and answer period with a panel of judges.
Each team member must participate equally in both the oral presentation and the question and answer period immediately following the team presentation.
Judges will complete a scoring sheet for each team presentation. An average score will be calculated for each team. Teams will be provided with their team score and feedback after the event.
Grading Rubric
About Daijha Flores
Daijha Flores is 14 years old and lives in Mesa, Arizona. She is a track and field athlete at the Lost Dutchman School and her specialty is the javelin throw. Her younger sister is also a track athlete and they look forward to competing because it helps them cope with stress. Their father is disabled and their mother is the sole income-earner for their family, as well as being the full-time caretaker for their father, as well as shuttling her and her sister to track meets. Due to prior hearing loss, Daijha received a cochlear implant in 2019. Recently, she and her mother and younger sister were traveling to a track meet in their minivan when their van was T-boned on the passenger side when a delivery van ran a stop sign. Daijha, seated in the left rear passenger seat, suffered injuries to her left side and her right hand and was evaluated in the Emergency Department and required follow-up care as a result of her injuries and possible damage to her cochlear implant device.
Read Daijha’s Emergency Department narrative (pdf)
Read Mom’s (Sophia) Post ED Narrative (pdf)
Read Little Sister’s (Andrea) Post ED Narrative (pdf)
Daijha’s home town of Mesa, Arizona
General City Information:
Mesa is located in Maricopa County, Arizona. It is the 38th-most populous city in the United States and the third-most populous city in Arizona after Phoenix and Tucson. Mesa lies to the east of Phoenix near the Superstition Mountains. Mesa is home to several colleges and universities and hosts the largest relief airport to Phoenix, the Mesa Gateway Airport.1
Mesa was founded by Mormon settlers in 1878. The original townsite was 1 mile square. Prior to this, the Hohokam people lived in the Salt River Valley and had built a canal system, part of which the settlers used for their first irrigation project in the area, and the first railroad arrived by 1895.2
Mesa’s diverse economy and key areas of strength include health care, education, aerospace and defense, tourism and technology industries. Some of the major employers in Mesa include Apple, AT&T, Banner Health, Boeing, Bridgestone and others.3
Mesa is home to many outdoor destinations and is the gateway to the Sonoran Desert and Tonto National Forest, among others and provides many opportunities to enjoy the arts and fine dining.4
Mesa Area Healthcare:
Mesa, Arizona is home to several hospitals from primary acute care, specialty and general hospital care. These include a network of hospitals through the Banner Health system, including Banner Desert (including Banner Children’s), Banner Baywood, Banner Heart, and Banner Gateway. Dignity Health and Honor Health also serve the Mesa Community.5
Economics:
“Mesa, Arizona’s cost of living is 4% higher than the national average.” Housing and utilities are 6% above the national average with the median home price at $566,308.6 The living wage for a household of 2 adults and 2 children (with only one parent working) is $90,480 annually.7
1 Wikipedia
2 City of Mesa
3 AZ Commerce
4 City of Mesa
5 Mesa Chamber.org
6 Payscale.com
7 Living Wage calculator
Daijha Flores’s Emergency Department Visit
14-year-old Daijha Flores presented to the Emergency Department following a motor vehicle accident in which the vehicle she was in was T-boned. Daijha presented with left-sided mouth pain, having difficulty hearing despite a left cochlear implant, pain and bruising over the left collarbone and hip, pain with a laceration on the right hand, and edema of the right 5th finger. ED findings included concussion without loss of consciousness; laceration of right hand; displaced fracture of the base of the 5th metacarpal bone of the right hand; left hip contusion; left clavicle contusion; tooth fracture and oral cavity laceration and unspecified sensorineural hearing loss establishing need for evaluation of cochlear implant device.
Physician/PA Emergency Department Notes
Patient Name: Flores, Daijha
DOB: 09/14/2012
Age: 14 years old
Gender: Female
Date of Service: 06/22/2026
CHIEF COMPLAINT
MVA (T-bone), head injury, facial injury, right hand laceration, collarbone pain, left hip pain.
HISTORY OF PRESENT ILLNESS (HPI)
Patient is a 14yo female with a past medical history significant for profound hearing loss who presents for evaluation after a motor vehicle T-bone collision which occurred earlier today. The patient was travelling to a track meet where she was to participate in the javelin throw when the mini-van vehicle she was riding in that was driven by her mother and also was carrying her 12-year-old sister was struck on the right-hand side by a delivery van that failed to yield at a stop sign. Speed of the travelling vehicles is unknown. EMS report states air bag did not deploy. Per the patient she was seated in left side passenger seat behind her mother and wearing her seatbelt at the time of the collision, and that when the collision occurred, she was slammed against the window on her left side, hitting her head. She also reports left sided mouth pain and notes she hit her mouth/teeth during the collision as well. The patient notes she wears a left cochlear implant for history of profound hearing loss and that she has had difficulty hearing since the time of the collision. She reports pain and bruising over her collarbone and left hip. Patient also reports that during the collision the left driver’s side middle passenger window shattered and she received a laceration on her right hand, which is her dominant hand. She is also reporting pain and swelling of the right 5th finger.
Past Medical History
- Profound sensorineural hearing loss
- left-sided cochlear implant recipient.
Family History
- Mother- Non-contributory
- Father- quadriplegia and secondary cognitive impairment
- Sister- Retinitis Pigmentosa
Social History
- Resides in Mesa, AZ in a home with mother, father and sister (12yo)
- Track and Field athlete (javelin thrower)
- Father is quadriplegic with secondary cognitive impairment following a prior disability. Mother is the sole financial provider and full-time home caregiver. Younger sister (Andrea, 12) has untreated, progressive Retinitis Pigmentosa and a speech articulation impediment (lisp). Family presents with an isolated social network and minimal external caregiving support.
REVIEW OF SYSTEMS
- General: no fever, no chills, no fatigue, no weakness, no weight changes
- HEENT: No vision changes, no blurred vision, no eye pain, possible damage to left-sided cochlear implant (physician could not be definitive). Decreased hearing noted. No tinnitus or rhinorrhea/otorrhea. No dysphagia, no odynophagia, no hoarseness. Maxillofacial: Severe pain along the left upper and lower jawline, continuous bleeding from the oral cavity, and structural instability of the left teeth.
- Respiratory: no shortness of breath, no coughing, no wheezing, no sputum production
- Cardiovascular: no chest pain or pressure, no palpitations, no dyspnea on exertion, no peripheral edema
- GI: positive nausea, no abdominal pain, no vomiting, no dysphagia no diarrhea, no constipation, no hematemesis, no melena
- Neurological: positive headache, positive dizziness, no vision changes, no weakness, no tremors, no numbness, no tingling, no syncope or LOC.
- Musculoskeletal: Positive point tenderness over the left clavicle, sharp localized pain along the left iliac crest (hip pointer), positive antalgic gait, and severe pain/swelling of the right dominant hand, no other joint pain or swelling, no muscle aches, no stiffness
- Genitourinary: no flank pain, no dysuria, no hematuria, no frequency or urgency, no urinary incontinence
- Integumentary: Positive bruising in area of seatbelt distribution and left hip, no rashes, no pruritus, no new skin lesions, no skin masses
- Endocrine: no heat or cold intolerance, no polydipsia or polyphagia
- Heme/Lymph: no easy bruising or bleeding, no swollen lymph nodes
- Allergic/immunologic: denies frequent infections, no seasonal allergies, no hives
PHYSICAL EXAMINATION
Vitals: BP: 118/74 | HR: 88 bpm | RR: 16 rpm | Temp: 98.6°F | SpO2: 99% on room air.
- General: Alert, visibly anxious, holding her right hand, leaning away from her left side. Cooperating with examination using visual tracking.
-
HEENT / Maxillofacial:
- Head: Contusion noted over the left temporal region. Scalp intact.
- Eyes: Pupils equal, round, and reactive to light (PERRLA). Extraocular movements intact (EOMI). Mild delayed convergence.
- Ears: Left external cochlear implant speech processor possible damage as noted by ED physician. Otoscopic exam reveals bilateral external auditory canals clear; tympanic membranes intact without hemotympanum, perforation, or erythema.
- Mouth/Jaw: Instability and segmental mobility of the left maxillary and mandibular alveolar ridges. Deep, 3.5 cm jagged laceration to the left buccal mucosa (inside of the cheek) with active venous oozing. Second molars are intact but tender to percussion; developing third molar buds cannot be clinically evaluated.
- Neck: Supple. Full range of motion. Trachea midline. Thyroid is normal size, smooth, and non-tender, no nodules. No cervical, supraclavicular, or axillary lymphadenopathy.
- Cardiovascular: Regular rate and rhythm, no murmurs, rubs or gallops. Pulses 2+ bilaterally throughout.
- Pulmonary: Clear to auscultation bilaterally, no wheezes, rales or rhonchi.
- Abdomen: Soft, non-distended. Bowel sounds normal active in all four quadrants. Non-tender to light and deep palpation. No hepatosplenomegaly, masses, or guarding/rebound tenderness.
-
Musculoskeletal:
- Clavicle: Ecchymosis and point tenderness over the left mid-shaft clavicle. No step-off, bony crepitus, or deformity.
- Left Hip: Severe ecchymosis and point tenderness along the anterior superior iliac spine (ASIS). Range of motion restricted by pain.
- Right Hand: Diffuse edema, dorsal ecchymosis over the fifth metacarpal. Tendon function (FDS/FDP) and digital capillary refill (<2s) are preserved.
- Full range of motion for all other major joints (shoulders, elbows, wrists, right hip, knees, ankles). No other joint effusion, warmth, erythema, or tenderness. Spine is straight with symmetric shoulders and iliac crests; negative Adams forward bend test (no spinal curvature or rib hump indicative of scoliosis). Gait is steady and smooth.
- Skin: Volar aspect reveals a 4.0 cm linear, deep subcutaneous laceration across the palmar crease of the dominant hand. Active bleeding controlled.
-
Neurological: Oriented to person, place, and time. Clear cranial nerves II-XII except for local cranial nerve VIII changes.
- MMSE: Noted deficits in short-term working memory, immediate recall, and sustained attention consistent with acute concussion.
- Psychiatric/Mental Status: Normal affect and pleasant mood. Speech is fluent, clear, and age-appropriate with normal articulation. However, patient speaks with a louder than normal volume. Thought processes are logical and goal-directed.
Diagnostics/Imaging
Result: CT Head & Maxillofacial (Non-contrast): No acute intracranial hemorrhage, midline shift, or mass effect. Linear, non-displaced fractures of the left maxillary and mandibular alveolar processes. Tooth buds of developing third molars are anatomically adjacent to the fracture lines; immediate displacement not seen.
Result: X-Ray Left Clavicle & Left Hip: No cortical disruption or fracture of the left clavicle; localized soft tissue swelling. Left hip films negative for bony fracture or dislocation; findings consistent with severe periosteal contusion (hip pointer).
Result: X-Ray Right Hand: oblique fracture of the base of the fifth metacarpal (Boxer's Fracture) with mild angulation.
ASSESSMENT AND PLAN:
-
V49.50XA V49.50XA (Passenger in unspecified motor vehicle accident, initial encounter)
- Patient underwent trauma evaluation and triage and individual injuries were evaluated and treated as described below. Patient instructed to follow up with PCP in 1-2 weeks for follow up of emergent care. Advised to return to the ED if any emergent or life-threatening symptoms occur.
-
S06.0X0A: (Concussion without loss of consciousness)
- Post concussion protocol reviewed with patient and caregivers. Patient was instructed to return to the ED immediately if any warning signs/symptoms occur.
- Referral for student to meet with Athletic Training Team at her school for evaluation and concussion protocol before any return to athletics.
- Referral to SLP/Communications team for evaluation of any post-concussion communication deficits
-
S61.411A: (Laceration without foreign body (Initial Encounter))
- Local anesthesia achieved via 1% Lidocaine without epinephrine. Irrigation with 500mL sterile normal saline. Wound explored; no foreign bodies or tendon disruptions noted. Closed with 10 interrupted 4-0 Ethilon (nylon) sutures. Sterile dressing applied. Patient instructed to follow up with PCP in 10-14 days for suture removal, or sooner if any signs/symptoms concerning for infection or wound dehiscence (reviewed with patient and caregiver today)
-
S62.347A: (Displaced fracture of the neck of the 5th metacarpal bone, right hand)
- Reduction of the fifth metacarpal fracture performed. Applied temporary splint with wrist neutral and 4th and 5th digits positioned with MCPs at 75 degrees flexion and IP joints positioned in extension. Distal neurovascular status verified as intact post-application.
- Referral to OT for evaluation and treatment plan; order included fabrication of custom, thermoplastic ulnar gutter splint.
-
S70.02XA: (Left hip contusion (Initial Encounter))
- Referral to PT for evaluation and treatment plan
-
S40.012A: (Contusion of left shoulder, initial encounter) – left clavicle
- Referral to PT for evaluation and treatment plan
-
S02.5XXA: (Fracture of tooth (traumatic), initial encounter for closed fracture)
- Referral to dental for urgent evaluation and treatment recommendations
-
S01.512A (Laceration without foreign body of the oral cavity, initial encounter)
- Local pressure applied to left buccal mucosa and hemostasis achieved. Refer to Dental to protect tissue borders.
-
H90.5: Unspecified sensorineural hearing loss
- Referral to Audiology for follow up of profound sensorineural hearing loss
- Referral to SLP for short-term aural rehabilitation services (e.g., augmentative and alternative communication) while awaiting cochlear implant repair.
-
Z96.21: Cochlear implant status
- Referral to Audiology for evaluation of cochlear implant device
-
Z59: Housing and economic circumstances
- Referral to Social Work for caregiver support and available social services and programs.
Provider Signature: Dudley Do-Right MMS, PA-C
Time of Discharge: 17:12 MST
Athletic Training Notes
Parient Name: Daijha Flores
Patient Gender: Female
Patient Age: 14 years old
Currently Live In: Mesa, AZ
School: Lost Dutchman School – has athletic trainer on site
Patient Sport Activity: Track, javelin throwing
Family Memebers of Patient:
- Mother: Sophia Flores
- Father (disabled): Victor Flores
- Younger sister (12 years old): Andrea Flores
History:
- Pt was in a car accident (T-bone) on way to track meet
- Was wearing seatbelt (no air bag deployment)
- Pt was slammed against the window on L side
- Has history of hearing loss (7 years) – profound sensorineural hearing loss; wears L-sided cochlear implant
- Complains of having difficulty hearing ED care team
- Complains of feeling something “different” with cochlear implant
- Pt seems worried about ability to continue to play sports
- Complains of L hip pain
- Complains of pain and swelling of R 5th finger
- No LOC
Observation:
- Ecchymosis noted in area of seatbelt distribution
Head
- Visual inspection of L ear revealed no ear drum rupture
- Ecchymosis over L temporal region
- PERRLA - Mild delayed convergence of pupils observed
- L external cochlear implant speech processor - visible crack and detached
- Otoscopic exam – bilateral external auditory canals clear
- 3.5 cm jagged laceration to L buccal mucosa (inside of cheek) with active venous oozing
Gait
- Antalgic gait observed
Hip
- Ecchymosis over L hip noted
Shoulder
- Ecchymosis over L mid-shaft clavicle
Hand
- Edema noted in R hand
- R hand diffuse edema
- Dorsal ecchymosis over 5th metacarpal
Palpation
(+)point tenderness over L clavivle
(+)sharp, localized pain along L iliac crest upon palpation
(+)pain on R hand when palpated without the splint
Special Tests
Head
- Positive for structural shift & external malfunction of implant housing of L side cochlear implant
- (+) decreased hearing
- (-)tinnitus, rhinorrhea/otorrhea
- (-)dysphagia
- (-)odynophagia
- (-)hoarseness
- Structural instability of L teeth
- (+)h/a
- (+)dizziness
- (-)vision changes
- Instability & segmental mobility of L maxillary & mandibular alveolar ridges
- 2nd molars intact but tender to percussion
- Cranial nerve VIII limitations – deficits in short-term working memory, immediate recall, and sustained attention
Shoulder
- (-)step-off, bony crepitus or deformity of L clavicle
Hip
- L Hip ROM limited by pain
Hand
- R hand Tendon function and capillary refill WNL
General Exam
- (-)respiratory exam
- (-)cardiovascular exam
- (+)nausea
- (-)MMT for weakness
- Full ROM WNL of neck
- Normal abdominal evaluation
Diagnosis:
Head
- Mild concussion w/o LOC
Face
- Dental Damage – L side (L Maxillary/Mandibular alveolar Fx, soft tissue lacerations)
- Laceration w/o foreign body of oral cavity
- Fx of tooth (traumatic)
- CT Results: linear, non-displaced fracture of L maxillary & mandibular alveolar processes
Shoulder
- L clavicle contusion
- X-Ray Results: No cortical disruption or fracture of the left clavicle; localized soft tissue swelling.
Hip
- L hip pointer
- X-Ray Results: Left hip films negative for bony fracture or dislocation; findings consistent with severe periosteal contusion (hip pointer).
Hand
- 5th metacarpal fx (splinted in ED with temporary splint)
- R hand laceration on palmar aspect (10 stitches)
- X-Ray Right Hand: Displaced, oblique fracture of the base of the fifth metacarpal (Boxer's Fracture) with mild angulation
Plan:
- Follow up on stitches
- Given crutches to use with ambulation
- Applied ulnar gutter fiberglass splint to 5th metacarpal bone of R hand
- L hip contusion (hip pointer)
- L shoulder contusion (L clavicle)
- Referrals necessary
Andrea - Sister
History
- Has retinitis pigmentosa
- Struggles with self-confidence
Diagnosis
- Grade 2 lateral ankle sprain
Audiology Notes
Date of Exam:
Patient Name: Daijha Flores
Date of Birth: 09/14/2012
Provider: N. Nelson, AuD
Chief Complaint: Evaluation of left cochlear implant function following a motor vehicle collision (MVC).
SUBJECTIVE (S)
The patient is a 14-year-old female with a history of profound left-sided sensorineural hearing loss status post left cochlear implant (CI) [Cochlear Americas] 2019. Daijha presents today for urgent evaluation after being involved in a motor vehicle collision on June 22, 2026, where their vehicle was T-boned on the right side. According to EMS, airbags did not deploy. They were evaluated at the Emergency Department immediately following the crash, where acute intracranial hemorrhage and cervical spine fracture were ruled out via non-contrast Head CT. Review of systems in the emergency department noted possible cochlear implant damage. Patient reports decreased hearing since the accident. She was diagnosed with an acute concussion, repaired a laceration on her right hand and discharged home. Other significant medical history includes a sister (12 years old) with retinitis pigmentosa.
Current Cochlear Implant Symptoms:
- Device Status: The patient reports that since the accident, the left CI external processor is causing sound distortion and her hearing has decreased.
- Site Pain: Mild to moderate, dull aching over the left mastoid and the subcutaneous receiver-stimulator bed. Denies sharp, throbbing pain.
- Aural Fullness / Tinnitus: None.
- Discharge: Denies clear fluid leakage (otorrhea or rhinorrhea) or bleeding from the ear canal.
OBJECTIVE (O)
Physical Examination:
- Otoscopy (Left): External auditory canal (EAC) is clear, without laceration, hemotympanum, or signs of cerebrospinal fluid (CSF) otorrhea. Tympanic membrane (TM) is intact, neutral, and translucent. No erythema or middle ear effusion.
- Mastoid & Implant Site Inspection:
- No visible lacerations or hematoma over the left mastoid surgical site.
- Palpation: Mild tenderness over the receiver-stimulator site. The internal device housing feels well-seated within the bony well; no macro-instability, step-off, or signs of significant sub-periosteal migration.
- The overlying skin is intact without erythema, warmth, breakdown, or excessive swelling. The internal magnet appears properly aligned beneath the skin.
Audiological & Device Evaluation (Internal/External):
- External Processor Inspection: Left speech processor shows minor external scuffing. Battery compartment is secure. Transmitting coil and cable are intact.
- Telemetry & Impedance Testing:
- Initial software connection established with the internal receiver-stimulator.
- Impedance telemetry shows all 22 electrode channels are within normal operational limits. No short circuits or open circuits detected.
- Neural Response Imaging (NRT) confirms neural responsiveness is stable compared to the patient's baseline from 10/05/2025 (date of last mapping appointment)
- Behavioral Testing (Aided): Word recognition testing (CNC words in quiet) with the left CI alone shows a mild, statistically non-significant drop compared to prior baseline (Currently 84% vs Baseline 92%), likely secondary to cognitive fatigue from the acute concussion.
ASSESSMENT (A)
- Left Cochlear Implant Functional Integrity: The internal receiver-stimulator, magnet, and electrode array are mechanically and electronically intact based on telemetry and transcutaneous palpation. No evidence of hard device failure, magnet displacement, or significant electrode migration at this time. Subtle behavioral testing variations are highly consistent with central cognitive fatigue rather than mechanical device degradation.
PLAN (P)
Cochlear Implant Management:
- Device Status: Cleared for continued use. The patient may continue wearing the left processor as tolerated.
- Acoustic Comfort: Given the patient's acute concussive syndrome, a temporary "concussion map" has been created and loaded to Program 1. T-levels and C-levels were re-measured and dynamic range was adjusted. Conservative adjustments were made and MAP was created for Program 1. Previous MAP was saved as Program 2 so patient can revert if needed.
- Precautions: Advised patient to monitor closely for changes in sound quality, sudden popping noises, or structural skin shifts over the device. If noted, they are instructed to power off the device and contact this clinic immediately.
Electronically signed by: N. Nelson, AuD
Dental Notes
Patient Name: Flores, Daijha
DOB: 09/14/2012 | Age: 14 years old
Gender: Female
Date of Service: 06/23/2026
Provider: Dr. Alex Mercer, DDS (Pediatric & Maxillofacial Dentistry)
CHIEF COMPLAINT
"My left jaw hurts, my teeth feel loose, and the inside of my cheek was bitten during the car accident."
HISTORY OF PRESENT ILLNESS (HPI)
Patient is a 14-year-old female presenting for urgent dental and maxillofacial evaluation after a motor vehicle collision (T-bone impact) on 06/22/2026. Patient was seated in the rear left passenger seat and sustained lateral head and facial impact against the vehicle window. Patient was initially evaluated and stabilized in the Emergency Department. She reports severe left-sided intraoral pain, continuous low-grade oozing, and structural instability/looseness of her left upper and lower teeth. Patient notes that the inside of her left cheek was severely pinched/chewed during impact. Additionally, she presents with a mild concussion, a right 5th metacarpal fracture (splinted), a right palmar laceration (10 sutures), a left hip pointer, a left clavicle contusion, and a possible damage to left-sided cochlear implant speech processor as noted by ED physician. Communication was conducted using clear visual tracking and written prompts due to acute hearing impairment and concussion protocols.
MEDICAL, DENTAL, & SOCIAL HISTORY
- Past Medical History: Profound sensorineural hearing loss (7 years) with left-sided cochlear implant; recent mild concussion.
- Past Dental History: No prior maxillofacial trauma; regular restorative care.
- Family & Social History: Student-athlete (track/javelin thrower) at Lost Dutchman School. Resides in Mesa, AZ, with mother (primary caregiver), father (quadriplegic/cognitively impaired), and younger sister (retinitis pigmentosa). Family experiences significant social isolation and stressors.
REVIEW OF SYSTEMS (MAXILLOFACIAL & INTRAORAL)
- Positive: Left-sided jaw pain, mobility of the left maxillary and mandibular segments, continuous venous oozing, localized tooth tenderness, and soft tissue pain in the left buccal mucosa.
- Negative: Dysphagia, odynophagia, hoarseness, airway compromise, fever.
PHYSICAL EXAMINATION
Extraoral Examination
- Facial/Head: Left temporal region contusion with mild localized edema. Temporomandibular joints (TMJs) non-tender bilaterally; range of motion within functional limits without clicking or deviation.
- Jaw/Symmetry: Facial asymmetry secondary to soft-tissue swelling of the left cheek. Palpation along the left inferior border of the mandible reveals localized point tenderness without step-off deformity.
Intraoral Examination
- Soft Tissue: 3.5 cm jagged, deep laceration across the left buccal mucosa (inside left cheek) with evidence of dental entrapment or bite injury from lateral impact. Venous oozing controlled.
-
Hard Tissue & Periodontium:
- Segmental Mobility: Instability and segmental mobility observed along the left maxillary and mandibular alveolar ridges.
- Dentition: Left second molars are intact but significantly tender to percussion. Developing third molar (wisdom tooth) buds cannot be clinically evaluated due to swelling and age. Occlusion is disrupted secondary to segmental displacement of the alveolar bone.
DIAGNOSTICS & IMAGING REVIEW
- CT Maxillofacial (ED Review): Linear, fractures of the left maxillary and mandibular alveolar processes. Developing third-molar tooth buds are anatomically adjacent to the fracture lines, with no immediate displacement observed.
- Intraoral Panoramic/Periapical Radiographs (In-Office): Confirm alveolar segmental fractures. No clinical root fractures or avulsions detected in the visible permanent dentition. Developing third molar buds remain intact but require monitoring.
DIAGNOSIS
- 1. S02.42XA: traumatic fracture of the maxillary alveolus
- S02.600A/S02.6 subcategory for the mandibular alveolar fracture.
- S01.512A Oral cavity laceration
- K08.89 Other specified disorders of teeth and supporting structures / occlusal disruption
Provider Signature:
Alex Mercer, DDS
Pediatric & Maxillofacial Dentistry
Time of Encounter: 10:30 MST
Occupational Therapy Evaluation Notes
Patient Name: Daijha Flores
Date of Birth: 09/14/2012
Visit No: 1- Initial evaluation
Setting: Outpatient hand therapy
Diagnosis: Right hand- Displaced, oblique fracture of the neck of the 5th metacarpal (Boxer’s Fracture) with mild angulation.
M.D. Orders: OT eval. and treatment. Fabricate orthoplastic, removable ulnar gutter orthosis; begin AROM only of hand and wrist with orthosis removed only for exercise. Orthosis required for any light hand use.
Precautions: Non-weight bearing (NWB) on right hand.
SUBJECTIVE
History of Present Condition/Mechanism of Injury:
Patient is a 14 yo female who was involved in a MVA on 6/22/2026; she was a restrained passenger on the left side passenger seat behind the driver. She sustained a 4.0 cm linear, deep subcutaneous laceration across the palmar crease of the dominant hand which required 10 sutures. Stitches were removed 10 days after injury by the hand surgeon who referred her to outpatient OT for hand therapy.
X-ray showed displaced fracture of the base of the 5th metacarpal bone, right hand. In the ED she underwent closed reduction of the fifth metacarpal fracture and application of an ulnar gutter fiberglass splint in a functional position. Patient had follow-up with the orthopedic specialist and presents with new script of OT eval. and custom orthotic fabrication
In addition to hand injuries, she also sustained a concussion without loss of consciousness, left hip contusion, left shoulder contusion, (no clavicle fracture identified), dental injuries, and sensorineural hearing loss with possible damage to cochlear implant in the left ear.
Her school athletic trainer is working with the patient in alliance with school district concussion protocol for return to sport and coordinating with teachers for return to learn readiness. She is currently attending all classes and working with her teachers on a modified assignment schedule.
Past Medical History (PMH):
This patient has a history of profound hearing loss over the last seven years and has a left-sided cochlear implant. She reported diminished hearing directly following the accident and is referred to audiology for evaluation of the device as well as SLP for short-term aural rehabilitation services while awaiting cochlear implant repair. SLP will also be working on memory and other cognitive impairments noted secondary to the concussion.
Social History:
Patient lives in a one-story home with her mother, father, and 12 yo sister. Her father has a history of TBI and high cervical SCI resulting in quadraplegia. He uses a power wheelchair and receives full-time care from the patient’s mother. The patient is active in Track and Field as a javelin thrower.
Primary Concern/Chief Complaint:
The patient is wearing the original fiberglass ulnar gutter splint fabricated in the ED. She reports that it is uncomfortable and leaves pressure marks at the ulnar wrist and side of her hand. It feels tight as swelling in her ulnar hand continues to increase although she is 10 days post injury.
She is able to use her dominant right hand for light activities of daily living (ADLs) with the fiberglass splint on such as self-feeding, oral hygiene, and grooming but reports pain is more pronounced at the end of the day. She is able to write with her right hand slowly, but states that she has difficulty with computer use for school. She is currently typing with her left hand and only radial right fingers for completing school assignments.
Handedness: Patient is Right hand dominant
Current Level of Function (PLOF):
Mobility: The patient is unable to use crutches due to right 5th metacarpal fracture and NWB status. Her left hip pain has decreased and she is able to walk short distances although antalgic gait persists.
Leisure/Interest: The patient would like to return to her track team when able. She expressed wanting to be able to get back to drawing and playing computer games which is now difficult with her hand fracture.
Pain Location
Worst: 6/10; Best: 2/10; Current: 4/10
Description of Pain: Aching pain in right hand at rest. Sharp pain in areas of pressure from the fiberglass splint. She has not tried to move her ulnar fingers on the right but knows that it will be initiated today during OT treatment.
Mental Status/Cognitive Function: Patient reports headaches from the concussion that are diminishing. She is doing better with her school work but reports ‘brain fog’ that makes it hard for her to remember what she is reading. Her teachers are working with her on a modified ‘return to learn’ assignment schedule.
Patient Goals: Regain ability to use right hand and return to full use for school work and javelin throwing.
OBJECTIVE
Patient Consent
Patient/Consent: X
Objective Measures
Quick Dash: 70.5% perceived disability. See attached report below
Cast/Splint Type: Orthoplastic forearm based ulnar gutter orthosis fabricated this date for right hand/wrist. Wrist neutral; 4th and 5th finger MCPs at 90 degrees flexion, IPs full extension. Good fit achieved; patient instructed in wear and care of orthosis including skin inspection and wearing schedule. She is to wear the orthosis at all times except during exercise, hand hygiene, and showering. She was independent with the don/doff of the orthosis.
Right palm laceration: Stitches removed by orthopedic surgeon. Healing well with no dehiscence or drainage. Does not affect motion of the hand or wrist. Tender to palpation around the incision.
Range of Motion
Right hand and wrist AROM is WNL at all joints
| Wrist AROM | Right |
|---|---|
| Extension | 35 degrees |
| Flexion | 40 degrees |
| Radial Deviation | 10 degrees |
| Ulnar Deviation | NT secondary to pain |
| Finger AROM | Right | ||
|---|---|---|---|
| MCP | PIP | DIP | |
| Thumb | WNL | WNL | |
| 2nd finger | WNL | WNL | WNL |
| 3rd finger | WNL | WNL | WNL |
| 4th finger | 25/60 degrees | 15/75 degrees | 0/40 degrees |
| 5th finger | 40/55 degrees | 20/55 degrees | 0/35 degrees |
Hand Strength: Not tested due to healing right 5th metacarpal fracture
Edema:
Wrist circumference:
Right: 19 cm
Left: 17 cm
Volumeter:
Right: 310 mL
Left: 265 mL
ASSESSMENT
Assessment/Diagnosis:
The patient presents with signs and symptoms consistent with a diagnosis of 5th metacarpal fracture, 10 days post injury. The newly fabricated orthosis fits well and will allow for the patient to have unobstructed movement thumb, index and middle fingers for light hand use for ADLs and school work. Edema and stiffness in the right hand decreases her ability to complete full AROM; she has a good understanding of her home exercises for gentle AROM and tendon gliding exercises to be done 3-4x/day with orthosis removed. Of most concern is her inability to actively extend the ring and small fingers. Extension lag may be due to scarring to adhesions of the extensor digitorum on the dorsal surface of the 5th metacarpal, persistent edema, and tightness from the healing palmar laceration. Follow-through of HEP should help with tendon glide and return to full motion of the right ulnar fingers.
Recommend skilled OT for hand therapy to work toward goals. We will begin with wrist and hand AROM and will begin gentle strengthening of the hand and wrist as per M.D. order as bone healing progresses.
Rehab Potential: Good
Problem List:
Pain with functional use of right hand
Decreased AROM of wrist and ulnar fingers on the right
Edema in right wrist and hand
Decreased functional hand use for ADLs and school tasks

Physical Therapy Notes
Name: Daijha Flores
Date of Birth: 09/14/2012
Diagnosis: left hip contusion and left shoulder contusion (primarily left clavicle)
Date of PT referral: June 22, 2026
Date of PT initial evaluation: June 29, 2026
SUBJECTIVE
Chief complaint: Nagging pain on left shoulder and hip, worse at end of day
History of Present Condition:
Patient is a 14 yo female who was involved in a motor vehicle accident (MVA) on June 22, 2026. The patient reported that she was a passenger at the time of the accident, seated behind the driver on the rear left side. She also reported wearing a seatbelt at the time of collision. She further states that the pain from her left hip and left shoulder were the result of the direct impact during the accident. The orthopedic surgeon's notes reported no underlying fracture on both left shoulder and left hip. The patient has also been prescribed Advil to be taken every 6 hours. She reports that her pain level intensity is dependent on time of day, worsening during late afternoons. She was also advised to apply ice several times a day and was encouraged to take frequent rest. When prompted, she reported her current pain level at 4/10 at rest, but can go as high as 6/10 when it gets too painful. She reports stepping on the left foot worsens left hip pain. She is also able to move the left shoulder “just a bit;” this has affected her daily activities at home, including bathing and dressing. She noticed that her movement has significantly changed since the time of the accident. The patient is right hand dominant. Other significant injuries from the MVA include closed reduction of the fifth metacarpal fracture, concussion without loss of consciousness, and dental injuries. She was prescribed a walker with a right platform attachment prior to being discharged from the hospital. She mentioned that she has far less energy at this point and using the assistive device has become cumbersome but helpful in decreasing pain. The patient reported to the writer that she is anxious about returning to playing as a track and field athlete (javelin thrower).
Past Medical Hx:
Profound sensorineural hearing loss
- left-sided cochlear implant recipient
Family Hx:
- Father- tetraplegic with secondary cognitive impairment
- Sister- retinitis pigmentosa
Social Hx:
- lives in Mesa, AZ in a home with mother, father and sister (12yo)
- Track and Field athlete (javelin thrower)
- Father is quadriplegic with secondary cognitive impairment following a prior disability.
- Mother is the sole financial provider and full-time home caregiver.
- Younger sister (Andrea, 12) has untreated, progressive retinitis pigmentosa and a speech articulation impediment (lisp)
OBJECTIVE
V/S: BP – 110/60 mmHg
HR – 60 bpm
RR – 14 cpm
Ocular inspection:
- Patient coherent and alert X 3 (time, place, and person)
- Ecchymosis noted on left clavicle
- Right hand edematous, hand splint noted (orthoplastic forearm based ulnar gutter orthosis)
Range of Motion (ROM) Testing:*
| Left shoulder | Left hip | |||
|---|---|---|---|---|
| Active | Passive | Active | Passive | |
| Flexion | 0-40 degrees | 0-43 degrees | 0-10 degrees, limited by pain | 0-12 degrees, limited by pain |
| Extension | Not tested, patient declined | Not tested, patient declined | 0-7 (modified testing positon due to discomfort) | 0-9 (modified testing positon due to discomfort) |
| External rotation | Not tested, patient declined | Not tested, patient declined | Not tested, patient declined | Not tested, patient declined |
| Internal rotation | Not tested, patient declined | Not tested, patient declined | Not tested, patient declined | Not tested, patient declined |
*Patient declined to have right hand ROM measured - “Please don’t touch it.”
Manual Muscle Testing (MMT):
All group muscles grossly graded 5/5, except for left shoulder and left hip, noted below:
| Left shoulder | Left hip | |
|---|---|---|
| Flexion | 2/5 (limited by pain in left clavicular area) | 2/5 (limited by pain in hip pointer area) |
| Extension | Not tested, patient declined | 2/5 |
| External rotation | Not tested, patient declined | 3/5 |
| Internal rotation | Not tested, patient declined | 3/5 |
Muscle palpation – tenderness noted left shoulder (clavicular area), left hip pointer area, and right hand.
ASSESSMENT:
PT Impression: Patient presents with limited left shoulder mobility and antalgic gait secondary to left hip pointer injury. Patient will benefit from several sessions of PT to address mobility issues, decrease pain level, and improve functional mobility and endurance. PT assessment and treatment for the right hand will be deferred until the patient consents.
Problem list:
- Limited ROM of left shoulder, particularly left clavicular area
- Limited ROM of left hip
- Decreased strength left shoulder
- Decreased strength left hip
GOALS:
Short term:
- Patient will improve ROM on left shoulder and left hip within 3 weeks of PT Rx
- Patient will improve strength left shoulder and left hip by a grade higher within 2 weeks of PT Rx
- Improve endurance using mobility aid
PLAN:
Frequency: 3X/week initially, tapering to 2X/week after 6 Rx sessions
Short term plan
- Educate patient on techniques to prevent worsening of left hand swelling
- Educate on energy conservation techniques
- AAROM left shoulder, all planes
- AAROM left hip, all planes
- isometric exercises for left shoulder
- isometric exercises for left hip
Medium term:
- Progression of above PT interventions
- Address right hand impairment
- Progress to appropriate assistive device when able
Signed: John Doe, PT
June 29, 2026
Public Health Notes
Public Health: Certified Health Education Specialist (CHES): Acts as Patient/Family Educator and Patient Navigator through the healthcare system and back into the community
PATIENT EDUCATOR/PATIENT NAVIGATOR NOTES FOR DISCHARGE PLAN PREPARATION: For providers:
RP - https://bestpractice.bmj.com/topics/en-us/1144
https://www.uptodate.com/contents/retinitis-pigmentosa-treatment
https://www.merckmanuals.com/professional/eye-disorders/retinal-disorders/retinitis-pigmentosa
Hearing loss/cochlear implants – https://jamanetwork.com/journals/jamaotolaryngology/article-abstract/2769941
https://www.fda.gov/medical-devices/implants-and-prosthetics/cochlear-implants?ftag=YHF4eb9d17
https://www.asha.org/Practice-Portal/Professional-Issues/Cochlear-Implants/
https://www.merckmanuals.com/professional/ear-nose-and-throat-disorders/hearing-loss/hearing-loss
https://www.cdc.gov/ncbddd/hearingloss/treatment.html
Concussion - https://www.cdc.gov/heads-up/hcp/providers/index.html
https://www.aafp.org/afp/2024/1000/practice-guidelines-concussion-in-sport
https://www.aap.org/en/patient-care/concussion/
https://www.cdc.gov/heads-up/guidelines/returning-to-sports.html
https://www.concussionalliance.org/recovery-guide-children-adolescents
https://www.neurologyadvisor.com/factsheets/concussion-grades/
Your roles as part of the IP team – work with other providers to:
-
PROVIDE PATIENT/FAMILY EDUCATION ON:
https://www.ama-assn.org/topics/patient-resources
Daijha/family – medical self-advocacy/speaking up to providers – https://www.ppcc-pa.org/toolkits-2/advocacy-toolkit
https://www.stlouischildrens.org/health-resources/pulse/teen-health-advocacy
https://www.npaf.org/
https://selfadvocacy.pitt.edu/sites/default/files/assets/Self-Advocacy%20Training%20For%20Patients.pdf
https://www.patientadvocate.org/explore-our-resources/
https://heartsandminds.nami.org/articles/medical-self-advocacy/Daijha/family – hearing loss - https://www.azdhs.gov/documents/prevention/womens-childrens-health/reports-fact-sheets/hearing-vision/HearingAids-ResourcesForParents_English.pdf
https://www.cdc.gov/hearing-loss-children/treatment/index.html
https://assets.cochlear.com/api/public/content/CAM-MK-PR-475-Cochlear-Implants-for-Children-Fact-Sheet.pdf
https://www.merckmanuals.com/home/searchresults?query=hearing%20loss&icd9=389;388.0;388.1&page=1&type=topicMake her hearing loss team - Typically includes an audiologist to assess and manage hearing devices, an otolaryngologist for medical and surgical treatment, and a speech-language pathologist to support communication development. Additionally, a psychologist may be included to address emotional and social needs, and a special education teacher can help with educational strategies.
Concussion/mild grade – return to sports/learning/recovery – https://www.concussionalliance.org/our-programs#patient-advocate-education
https://www.nationwidechildrens.org/specialties/concussion-center/concussion-toolkit/return-to-learn
https://www.cdc.gov/heads-up/guidelines/index.html
https://cbirt.org/sites/cbirt.org/files/resources/ocamp_yso_all.pdf
https://www.concussionalliance.org/Make her concussion team - Youth concussion clinical team should include sports medicine specialists, neurologists, psychologists, physical therapists, occupational therapists, and athletic trainers to address the various aspects of concussion care and recovery.
Andrea/family - RP – https://my.clevelandclinic.org/health/diseases/17429-retinitis-pigmentosa
https://www.hopkinsmedicine.org/health/conditions-and-diseases/retinitis-pigmentosa
https://www.aao.org/eye-health/diseases/what-is-retinitis-pigmentosaMake her RP – team: Managing RP requires more than just an eye doctor. A multidisciplinary care team ensures all your needs—physical, functional, and emotional—are met. Retinal Specialist: To monitor the health of your retina and keep you informed about clinical trials. Low Vision Specialist: An optometrist who specializes in prescribing the right magnification and technology for your specific vision. Orientation & Mobility (O&M) Specialist: A trainer who teaches you how to move safely through the world . Mental Health Counselor: To support you through the emotional transitions of vision loss.
Mom – caregiver/mental health self-care - https://www.health.harvard.edu/blog/self-care-for-the-caregiver-201810171716
https://www.everydayhealth.com/emotional-health/self-care-for-caregivers/
https://mhanational.org/caregiving/
https://adaa.org/find-help/by-demographics/caregivers -
ADVOCATE FOR ACCESS AND PROVIDE PATIENT/FAMILY EDUCATIONAL RESOURCES ON:
Medical self-advocacy/speaking up to providers educational materials - https://wapave.org/healthcare-transition-and-medical-self-advocacy/
https://www.ppcc-pa.org/toolkits-2/advocacy-toolkit
https://amchp.org/resources/teen-self-advocacy-how-to-be-your-own-healthcare-advocate/Concussion/mild grade – return to sports/learning/recovery educational materials- https://concussionandcte.org/wp-content/uploads/2024/09/Concussion-Guidebook-for-Patients-and-Caregivers.pdf
https://concussionhub.org/
https://www.neuropt.org/docs/default-source/cpgs/concussion/concussion-kt-clinician-resources/patient-handout_final.pdf?sfvrsn=b6765d43_0
https://www2.gov.bc.ca/assets/gov/health/practitioner-pro/bc-guidelines/concussion-mbti-appendix-d.pdf
https://www.bianc.net/resources/handouts/RP – patient education materials: https://biausa.org/public-affairs/media/concussion-awareness-infographics
https://www.merckmanuals.com/home/eye-disorders/retinal-disorders/retinitis-pigmentosa
https://www.nei.nih.gov/eye-health-information/eye-conditions-and-diseases/retinitis-pigmentosa
https://www.fightingblindness.org/patient-resources
https://incitefulmed.com/resources/guides/retinitis-pigmentosa-comprehensive-guide/
https://www.asrs.org/patients/patient-education-materials
https://isgedr.com/wp-content/uploads/2015/01/understand-retinitis-pigmentosa-uofm.pdfCaregiver mental health self-care resources - https://dscc.uic.edu/browse-resources/caregiver-mental-health-toolkit/
https://mhanational.org/resources/tools-and-resources-for-caregivers/
https://www.nia.nih.gov/toolkits/caregiving
https://www.caregiveraction.org/toolbox/Hearing loss materials - https://www.hear4hope.org/resources
https://www.aidthesilent.com/wp-content/uploads/2025/04/AidTheSilent-Resource-Booklet-Web.pdf
https://www.cdc.gov/hearing-loss-children/communication-resources/links-to-other-resources-on-hearing-loss.html
https://nationaldeafcenter.org/resources/ -
RECOMMEND PATIENT/FAMILY COMMUNITY SUPPORT SERVICES
RP/vision loss – Ex. Social media support groups: https://www.facebook.com/groups/jacquelinemeek/
https://www.juliettefoundation.org/
https://www.fightingblindness.org/chapters - https://www.fightingblindness.org/chapters/arizona- Arizona chapter - https://eyespy.org/media/groups/ - Arizona Chapter; https://viewfinderlowvision.com/peer-support-groups - Mesa;Cochlear implants/hearing loss - https://www.acdhh.org/
https://ageofaccess.az.gov/
https://www.hearingloss.org/get-involved/hlaa-chapters/find-a-chapter/
https://www.atarizona.com/pdf/AZhear.pdf
https://hlaawestvalleyaz.org/hearing-help/
https://www.hearingloss.org/Financial support – health - https://www.mesaaz.gov/Resident-Resources/Community-Support-Programs
https://www.needhelppayingbills.com/html/arizona_assistance_programs.html
https://azretinacare.com/patients/financial-information/
https://www.thehelplist.com/city/az-mesa
https://www.findhelp.org/money/financial-assistance--mesa-azFinancial support – low vision https://www.asrs.org/patients/patient-assistance-resources
https://preventblindness.org/vision-care-financial-assistance-information/
https://lowvision.preventblindness.org/financial-assistance-for-eye-care/
https://www.asrs.org/patients/patient-assistance-resourcesFinancial support - hearing loss - https://asuspeechandhearingclinic.org/services/adult-hearing-and-balance/hearing-healthcare-assistance-program
https://www.acdhh.org/hard-of-hearing/hearing-aids/
https://www.hearingloss.org/find-help/financial-assistance/
https://www.cms.gov/medicare-coverage-database/view/ncd.aspx?NCDId=245 -
Coordinate sisters’ care while at school with School Health Services and Counseling, Psychological, and Social Services components of the WSSC Model
https://www.cdc.gov/whole-school-community-child/about/index.html and https://www.cdc.gov/whole-school-community-child/about/components-of-wscc.html
Health services - Educate students and their caregivers about chronic conditions and coordinate care with external health care providers. Train appropriate school staff on how to provide resources that support students with chronic health conditions.
Counseling, psychological, and social services - Help students with chronic health conditions during transitions, such as changes in schools or family structure. Provide or refer students and families to school- and community-based counseling services.
Daijha – cochlear implants – tool for schools: https://www.advancedbionics.com/us/en/home/learn/kids/tools-for-schools ; what educators need to know - https://www.fda.gov/medical-devices/cochlear-implants/what-educators-need-know ; students with hearing loss - https://showmeschoolhealth.org/resources/students-with-hearing-loss-or-deafness/ + https://cdn.rileychildrens.org/resources/cochlear-implant-program-information-for-teachers-and-other-school-professionals-160505.pdf
Andrea - RP at school- https://www.pathstoliteracy.org/wp-content/uploads/2022/06/Classroom_adaptations_for_students_with_low_vision.pdf
https://nelowvision.com/adapting-the-classroom-for-children-with-low-vision-practical-strategies-for-inclusive-learning/
https://teachers.institute/higher-education-the-psycho-social-context/supporting-visually-impaired-students/
https://childrenwithspecialneeds.com/supporting-children-with-visual-impairments-in-school/ -
Conduct health counseling with family and coordinate community mental health support/resources.
https://www.freementalhealthservices.org/ci/az-mesa
https://www.mentalhealthlistings.net/clinics/arizona/mesa.html
https://mentalhealthproviders.com/cities/mesa-arizona-mental-health-and-substance-abuse-facilities/
https://www.freeclinics.com/cit/az-mesa
https://www.freementalhealth.us/services/mesa_community-bridges-inc
Speech-Language Pathology Notes
Patient Name: Flores, Daijha
DOB: 09/14/2012
Age: 14 years old
Gender: Female
Individuals present during the assessment: Daijha Flores (patient) and Sophia Flores (mother)
Referral Diagnoses:
- S06.0X0A: Concussion without loss of consciousness
Background Information
Daijha is a right-handed 14- year-old female referred by her primary care physician to assess cognitive-linguistic concerns after sustaining a head injury during a motor vehicle accident two weeks ago. During the accident, she sustained a laceration to the left buccal mucosa. The client’s past medical history is significant for profound hearing loss; her left cochlear implant was damaged at the time of the accident and is reportedly currently functioning well. Daijha attends Lost Dutchman school and is a student athlete. Per chart review, the Mini-Mental Status Exam (MMSE) was administered in the emergency department on 06/22/2026; Daijha had deficits with short-term working memory, immediate recall, and sustained attention. Prior to the concussion, Daijha did not have concerns with cognitive-linguistic function.
Assessment Information
Presenting Concern:
- Subjective patient report: “I just don’t feel like myself. I can’t focus and can’t remember things. I’m tired all the time.”
- Subjective caregiver report (Sophia): “She’s having trouble remembering things at home and at school. Before this happened, she was a straight A student. Recently, she’s been getting Cs, and she forgot to turn in a history paper…that’s not like her.”
Screenings:
- Audiologic: pure-tone screening not completed. Refer to Dr. Nelson’s notes for hearing status. Sophia reported that Daijha had an upcoming appointment scheduled with her audiologist and denied present concerns with hearing.
- Speech: passed screening criteria. Additionally, no patient/family concerns were reported.
- Swallowing: passed screening criteria. Additionally, no patient/family concerns were reported.
- Expressive and Receptive Language: passed screening criteria. Additionally, no patient/family concerns were reported.
Formal/Informal Assessment Results
-
Oral Peripheral Examination
- Lips, tongue, and velum: strength, speed, and range of motion were WNL.
- Jaw: mildly reduced strength, speed, and range of motion.
- Face, oral cavity, head, neck: symmetrical at rest and during speech.
- Adequate sensation of face and oral cavity.
- Adequate respiration and breath support for speech.
- Additional notes: Oral mucosa was aberrant on the left; consistent with the documented laceration.
-
Repeatable Battery for the Assessment of Neuropsychological Status (RBANS), Version A
- Standardized administration procedures were followed. Individual subtest scores were converted into scaled scores or percentile groups. Subtest raw scores were used to compute index scores for the five domains. Index scores have a mean of 100 and a standard deviation of 15. A total score was computed by combining the five index scores.
-
Subtests and descriptors based on scaled scores (+ denotes a relative strength; - denotes a relative weakness)
Subtest Classification List Learning- Low average Story Memory- Extremely low Figure Copy+ Average Line Orientation+ Low average Picture Naming+ Very superior Sematic Fluency+ Low average Subtest Classification Digit Span+ Average Coding- Borderline List Recall+ Average List Recognition- Extremely low Story Recall- Borderline Figure Recall+ Average -
Index scores and interpretations
Index Score Confidence Interval (90%) Percentile Descriptor Immediate Memory 70 63-77 2 Borderline Visuospatial/Constructional 93 78-108 32 Average Language 116 105-127 86 High Average Attention 77 66-88 6 Borderline Delayed Memory 59 49-69 0.3 Extremely low - Daijha’s total scale score was 79, indicative of mild-moderate deficits.
Resources
Workshop Recordings
Workshop 1: Whole Person Healthcare
Workshop 2: Roles & Responsibilities
Workshop 3: Cochlear Implants
Watch an example of a past team presentation
Related Article: (Coming Soon)
Learn more about the roles and responsibilities of the care providers
Athletic Trainers: Athletic Trainers use a medical based model to provide comprehensive patient care in the domains of prevention; clinical evaluation and diagnosis; immediate and emergency care; treatment and rehabilitation; and organization and professional health and well-being. Athletic Trainers are highly qualified, multi-skilled health care professionals who collaborate with physicians to provide total patient care. Athletic Trainers work under the direction of a physician as prescribed by state licensure statutes.
Learn more at: http://www.nata.org/
Audiologist: "An audiologist is a person who, by virtue of academic degree, clinical training, and license to practice, is uniquely qualified to provide a comprehensive array of professional services related to the identification, diagnosis and treatment of persons with auditory and balance disorders, and the prevention of these impairments. Audiologists serve in a number of roles including primary service provider, clinician, therapist, teacher, consultant, researcher and administrator. In addition, the supervising audiologist maintains legal and ethical responsibility for all assigned audiology activities provided by audiology assistants and audiology students."
Source: Academy of Doctors of Audiology
Counselor: What is a professional counselor?
“Professional counselors help people gain personal insights, develop strategies and come up with real-life solutions to the problems and challenges they face in every area of life. As trained and credentialed professionals, they accomplish this by getting to know clients, by building safe, positive relationships and suggesting tools and techniques they believe will benefit clients.”
Learn more at: https://www.counseling.org/mental-health-counseling/what-is-counseling
Dentist: What is a Dentist?
You will find an interesting article here about the important interconnection between oral health and systemic health. So don't forget the importance of collaborating with the dentist!
Doctor of Osteopathic Medicine: “Doctors of Osteopathic Medicine use a unique whole-person approach to help prevent illness and injury.
Accounting for approximately 11% of all physicians in the United States, Doctors of Osteopathic Medicine, or DOs, bring a unique, patient-centered approach to every specialty across the full spectrum of medicine. They are trained to listen and partner with their patients to help them get healthy and stay well.”
Learn more at: https://osteopathic.org/what-is-osteopathic-medicine/what-is-a-do/
Nursing:
Registered Nurses
“Registered nurses (RN) form the backbone of health care provision in the United States. RNs provide critical health care to the public wherever it is needed.
Key Responsibilities
- Perform physical exams and health histories before making critical decisions
- Provide health promotion, counseling and education
- Administer medications and other personalized interventions
- Coordinate care, in collaboration with a wide array of health care professionals”
Learn more at: https://www.nursingworld.org/practice-policy/workforce/what-is-nursing/
Occupational Therapy: “Occupational therapy is the only profession that helps people across the lifespan to do the things they want and need to do through the therapeutic use of daily activities (occupations). Occupational therapy practitioners enable people of all ages to live life to its fullest by helping them promote health, and prevent—or live better with—injury, illness, or disability.
Common occupational therapy interventions include helping children with disabilities to participate fully in school and social situations, helping people recovering from injury to regain skills, and providing supports for older adults experiencing physical and cognitive changes.
Occupational therapy practitioners have a holistic perspective, in which the focus is on adapting the environment and/or task to fit the person, and the person is an integral part of the therapy team. It is an evidence-based practice deeply rooted in science.”
See also: https://www.aota.org/career/become-an-ot-ota/about-the-profession
Learn more at: AOTA.org
Physical Therapist: Physical therapists are movement experts who optimize quality of life through prescribed exercise, hands-on care, and patient education. After making a diagnosis, physical therapists create personalized treatment plans that help their patients improve mobility, manage pain and other chronic conditions, recover from injury, and prevent future injury and chronic disease.
Physical therapists empower people to be active participants in their own treatment, and they work collaboratively with other health professionals to ensure patients receive comprehensive care. Physical Therapy entry-level educational programs are at the doctoral level with subsequent educational opportunities for fellowship and residency. Physical therapists work in a wide range of specialty areas for which they can obtain specialty certification e.g. acute care, aquatics, cardiovascular & pulmonary, geriatrics, home health, neurology, oncology, orthopedics, pediatrics, sports, and women's health.
See also: https://www.apta.org/your-career/careers-in-physical-therapy/becoming-a-pt
Learn more at: APTA.org
Physician Assistant: What is a PA?
“PAs (physician associates/physician assistants) are licensed clinicians who practice medicine in every specialty and setting. Trusted, rigorously educated and trained healthcare professionals, PAs are dedicated to expanding access to care and transforming health and wellness through patient-centered, team-based medical practice.”
Learn more at: https://www.aapa.org/about/what-is-a-pa/
Social Worker: The profession of social work aims to improve functioning and overall well-being within individuals, families, organizations, and communities through change efforts. With a focus on the poor, the oppressed, and the vulnerable, social sciences such as sociology, psychology, political science, public health, economics, law, community and organizational change, are applied. Needs assessments are completed and interventions are planned to solve personal and social problems within client systems to enhance social change. Social work practice is often divided into three levels. Micro-work involves working directly with individuals and families, such as providing individual counseling/therapy or assisting a family in accessing services. Mezzo-work involves working with groups and communities, such as conducting group therapy or providing services for community agencies. Macro-work involves fostering change on a larger scale through advocacy, social policy, research development, nonprofit and public service administration, or working with government agencies. Professional training requires a master’s degree and most states require professional licensure. Social Workers are employed in a variety of settings including healthcare, government agencies education, corrections, public health, and public policy.
Source: Wikipedia
Speech Language Pathologist: Speech-language pathologists (SLPs) work to prevent, assess, diagnose, and treat speech, language, social communication, cognitive-communication, and swallowing disorders in children and adults.
Learn more at: https://www.asha.org/Students/Speech-Language-Pathology/
THE PUBLIC HEALTH EDUCATOR/PATIENT EDUCATOR’S ROLES AND RESPONSIBILITIES
PUBLIC HEALTH EDUCATION: CERTIFIED HEALTH EDUCATION SPECIALISTS [CHES]:
The U.S. Department of Labor – Bureau of Labor Statistics (BLS) has a classification of health educator and defines health educators (SOC 21-1091) as those that provide and manage health education programs that help individuals, families, and their communities maximize and maintain healthy lifestyles. Health Educators collect and analyze data to identify community needs prior to planning, implementing, monitoring, and evaluating programs designed to encourage healthy lifestyles, policies, and environments. They link health systems, health providers, insurers, and patients to address individual and population health needs. They may serve as a resource to assist individuals, other health professionals, or the community, and may administer fiscal resources for health education programs.
RESPONSIBILITIES/COMPETENCIES OF CHES:
| Area I: Assessment | Area II: Planning | Area III: Implementation |
| Area IV: Evaluation | Area V: Research | Area VI: Advocacy |
| Area VII: Communication | Area VIII: Administration and Management | Area IX: Ethics, Leadership, and Professionalism |
CHES IN HEALTHCARE
Individuals who hold the CHES® and MCHES® certifications have versatility and skillsets to practice in many different career settings, across the country and even overseas. Job settings were identified in the Health Education Specialist Practice Analysis (HESPA) include the following: Community/non-profit, Healthcare/Hospitals, Government, School Health, Academia/Universities, and Business/Worksite. Job titles in the hospital and healthcare sector can vary. Some common titles include Community Benefits Manager, Outreach Manager, Patient Educator or Program Manager, Patient Navigator, Wellness Coordinator, and Health Educator. Health Education Specialists in the Health Care setting may perform the following duties:
- Deliver and assess health education programs
- Coordination and outreach
- Enrollment and initial health assessments
- Motivate others to initiate behavior change
- Communicate/liaise with primary care physicians, hospitals and other health care providers
- Plan for health education interventions
- Translate medical and health education material for dissemination to client/patient
Brief IPE-training module with sample case